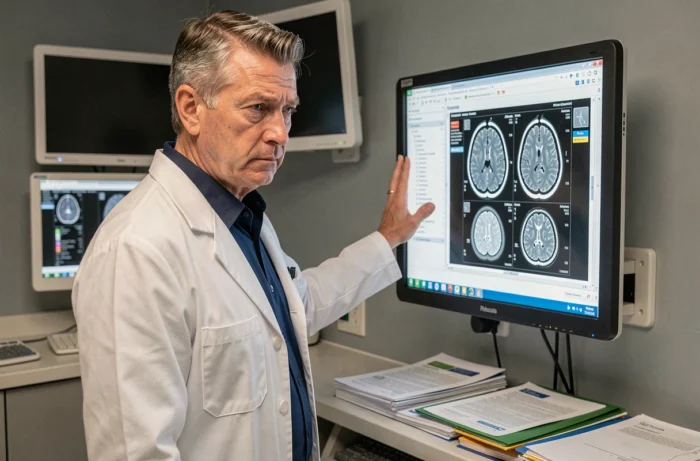
An MRI report mentioning a Fazekas score of 2 often triggers disproportionate concern. In practice, this intermediate grade of vascular leukopathy indicates confluent lesions of the white matter, without the number alone allowing for any predictions about remaining lifespan. What truly weighs on the prognosis are the associated vascular pathologies, the rate of functional decline, and the quality of medical follow-up.
Microbleeds and anticoagulants: the parameter that MRI alone does not summarize
There is often a focus on the hyperintensities of the white matter, but the presence of cerebral microbleeds radically changes the prognosis. These micro-bleeds, detected by specific MRI sequences, are not included in the Fazekas score. They alter the balance between the prevention of ischemic stroke and the risk of cerebral hemorrhage.
In practical terms, a patient classified as Fazekas 2 who is taking an anticoagulant for atrial fibrillation does not present the same risk as a patient without microbleeds. The therapeutic decision must integrate this individual parameter, not just the grade of leukopathy.
Superficial cortical siderosis, another visible marker on MRI, adds an additional level of complexity. When these signs coexist with a Fazekas 2, specialists’ opinions vary on the appropriateness of maintaining standard antithrombotic treatment. Several factors that influence life expectancy with Fazekas 2 leukopathy are precisely related to these associations of lesions that the score alone does not capture.
Atrial fibrillation and Fazekas 2 leukopathy: a duo to monitor
Atrial fibrillation is a major independent factor for deterioration. It exposes patients to cerebral embolisms that can rapidly impair functional and cognitive abilities, beyond what the white matter lesions would suggest.
Combined vascular leukopathy and atrial fibrillation increase the risk of stroke. One might think that a Fazekas 2 systematically contraindicates anticoagulants due to the fear of cerebral hemorrhage. The reality is more nuanced: the benefit of embolic prevention must be weighed against the hemorrhagic risk specific to each patient.
The elements that matter in this assessment:
- The number and location of microbleeds visible on gradient echo or susceptibility-weighted MRI sequences
- Blood pressure control, the main modifiable lever to slow the progression of white matter lesions
- The presence of other small vessel abnormalities (lacunes, dilated perivascular spaces) that inform about overall vascular involvement
- Renal status and coagulation profile, which modify the benefit-risk ratio of any antithrombotic treatment
Functional trajectory: a more reliable indicator than isolated MRI
A Fazekas 2 on two MRIs spaced three years apart does not have the same meaning depending on whether the patient walks normally or has already fallen several times. The functional trajectory provides better insight into prognosis than the radiological score.
In concrete situations, it is observed that walking speed, postural balance, and autonomy in daily tasks more accurately reflect the future risk of dependency. A Fazekas 2 patient with stable walking and preserved cognitive functions does not have the same outlook as a patient of the same grade who already exhibits attention disorders and difficulties organizing tasks.
Cognitive deficits to detect early
The first signs are not always dramatic. We are not necessarily talking about clear memory losses, but rather about slowed information processing and executive difficulties: planning a complex meal, managing a budget, following a conversation with multiple speakers.
These deficits, when they gradually set in for a Fazekas 2 patient, point towards an increased risk of vascular dementia. Early diagnosis of these disorders allows for tailored management (cognitive stimulation, rehabilitation, treatment adjustments) before the loss of autonomy sets in.
Control of vascular factors: what truly slows progression
We cannot make the existing white matter lesions disappear. The goal is to prevent their extension to a Fazekas 3 stage, where the lesions become diffuse and the risk of cognitive decline significantly increases.
Controlling high blood pressure remains the most documented lever. Poorly controlled blood pressure accelerates small vessel disease and promotes the appearance of new lesions. Diabetes, high cholesterol, and smoking also worsen the overall vascular picture.
Physical activity and cognitive reserve
Regular physical exercise acts on several fronts simultaneously: it contributes to blood pressure control, improves cerebral perfusion, and maintains functional capacities. Walking thirty minutes a day has a measurable effect on balance and speed of movement, two direct prognostic markers.
Intellectual and social stimulation plays a complementary role. A brain with good cognitive reserve compensates better for vascular lesions. This does not mean that the damage is erased, but that the threshold at which symptoms become disabling is pushed back.
- Regular blood pressure monitoring with personalized targets based on age and comorbidities
- Comprehensive vascular assessment (blood sugar, lipid profile, renal function) at least once a year
- Targeted neuropsychological evaluation if cognitive complaints or behavioral changes arise
The Fazekas 2 score is neither a sentence nor a negligible detail. It is a warning signal that makes sense when linked to microbleeds, atrial fibrillation, functional trajectory, and control of vascular risk factors. Life expectancy with leukopathy of this grade depends less on the number displayed in the report than on the rigor of overall follow-up and the ability to act on each modifiable factor.


